
Weekend Sale - Special 75% Discount Offer - Ends in 0d 00h 00m 00s - Coupon code: 75onlydt

CCDS Questions and Answers

Question # 6

After a month of intermittent antibiotic use, the patient is admitted. An infectious-control physician documents a diagnosis of Clostridium difficile in the inpatient medical record. Which domain of the MOST current Hospital Value-Based Purchasing program would this diagnosis impact?

A.

Clinical care

B.

PSI 90 data

C.

Hospital-acquired infection

D.

Safety outcome

Full Access
Question # 7

A CDI manager finds that cardiology providers receive repeated queries for heart-failure acuity and type. Which educational intervention is MOST appropriate?

A.

Send all providers the entire ICD-10-CM code book

B.

Provide cardiology-specific education using the department's own documentation trends and clinical examples

C.

Stop issuing heart-failure queries for one month

D.

Tell providers that unspecified heart failure reduces reimbursement

Full Access
Question # 8

A CDI specialist's working MS-DRG differs from the final coder-assigned MS-DRG in 18% of reviewed cases. What is the BEST initial management response?

A.

Assume the coding department is incorrect

B.

Perform a structured reconciliation analysis to determine the causes of the mismatches

C.

Require coders to use the CDI working DRG

D.

Exclude mismatched cases from CDI statistics

Full Access
Question # 9

A wound care nurse documents an assessment and care of a pressure ulcer. For coding purposes, the wound care nurse's documentation can be used to assign which of the following?

A.

POA status

B.

The diagnosis

C.

Location

D.

Stage

Full Access
Question # 10

A patient is admitted with hypertension and acute systolic heart failure. The provider does not explicitly link the two conditions and does not state that they are unrelated. Which coding principle applies?

A.

Hypertension and heart failure must always be coded separately unless the physician states “hypertensive”

B.

ICD-10-CM presumes a relationship between hypertension and qualifying heart disease unless documented as unrelated

C.

Acute heart failure cannot be associated with hypertension

D.

A relationship may only be recognized when hypertension is the principal diagnosis

Full Access
Question # 11

A patient underwent open small bowel resection with anastomosis for colon cancer. The physician notes, "Post-op ileus, awaiting return of bowel function." Which of the following actions should a CDI specialist take FIRST?

A.

Apply a secondary diagnosis code for postoperative ileus

B.

Assign a complication code along with the code for postoperative ileus

C.

Query if the ileus was a postoperative complication or expected outcome

D.

Discuss the matter with the physician advisor or the CDI manager

Full Access
Question # 12

Which of the following principal diagnoses groups to MS-DRG 884, Organic Disturbances and Intellectual Disability?

A.

Alzheimer's dementia

B.

Alcohol-induced dementia

C.

Wernicke dementia

D.

Vascular dementia

Full Access
Question # 13

A patient is admitted with chest pain and borderline elevation of troponins. The patient also reports a history of GERD. The physician documents that the chest pain is “likely GI in origin” and prescribes omeprazole. Based on the clinical indicators, which of the following actions should the CDI specialist take?

A.

Query for chest pain due to AMI

B.

Query for the condition requiring admission

C.

No query needed, GERD is the principal diagnosis

D.

No query needed, chest pain is the principal diagnosis

Full Access
Question # 14

The documentation is insufficient to determine whether a reportable diagnosis was present at the time of inpatient admission. Which POA indicator represents this situation?

A.

Y

B.

N

C.

U

D.

W

Full Access
Question # 15

The attending physician documents “severe protein-calorie malnutrition.” The dietitian's assessment documents normal nutritional intake, stable body weight, no fat loss, and no muscle wasting. What should the CDI specialist do?

A.

Accept the diagnosis because it was documented by the physician

B.

Delete the diagnosis

C.

Submit a clinical validation query

D.

Ask the dietitian to change the assessment

Full Access
Question # 16

The table below shows physician performance:
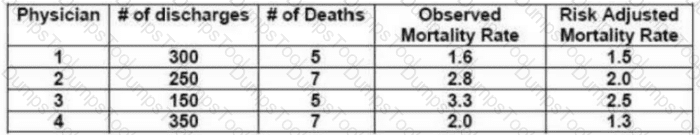
Question # 16

Which of the following physicians will have the most favorable mortality rate on a public website, such as Healthgrades.com?

A.

1

B.

2

C.

3

D.

4

Full Access
Question # 17

Respiratory failure is documented in a patient's initial progress notes. There are no clinical indicators in the record to support this diagnosis. According to the AHIMA/ACDIS Practice Brief Guidelines for Achieving a Compliant Query Practice, the MOST appropriate action by the CDI specialist is which of the following?

A.

Assign a code for respiratory failure

B.

Do not assign a code for respiratory failure

C.

Query the provider for validation of the diagnosis

D.

Review for documentation of CPAP to support respiratory failure

Full Access
Question # 18

A CDI team identifies that orthopedic surgeons frequently document “postoperative anemia” without specifying whether blood loss is acute, expected, chronic, or clinically insignificant. What is the BEST educational strategy?

A.

Provide targeted education using deidentified orthopedic cases and clinically relevant documentation examples

B.

Send surgeons a complete list of all anemia ICD-10-CM codes

C.

Tell surgeons to document acute blood loss anemia on every postoperative patient with decreased hemoglobin

D.

Stop querying postoperative anemia to reduce physician burden

Full Access
Question # 19

The physician evaluates a postoperative wound infection but states, “I cannot clinically determine whether the infection was already developing at admission or began after admission.” Which POA indicator MOST accurately reflects this provider determination?

A.

Y

B.

N

C.

U

D.

W

Full Access
Question # 20

A patient's hemoglobin decreases from 13.1 g/dL before surgery to 7.4 g/dL afterward. Estimated intraoperative blood loss is 1,200 mL, and the patient receives two units of packed red blood cells. The physician documents only “postoperative anemia.” Which clarification is MOST appropriate?

A.

Acute blood loss anemia versus another explanation for the anemia

B.

Hemolytic anemia only

C.

Chronic iron deficiency anemia only

D.

No clarification because transfusion establishes the diagnosis

Full Access
Question # 21

A patient with COPD normally has a PaCO₂ of approximately 45 mmHg. The patient is admitted with increasing somnolence and respiratory distress. Arterial blood gas results are pH 7.27, PaCO₂ 68 mmHg, and PaO₂ 58 mmHg. BiPAP is initiated. Which condition is MOST appropriate for the CDI specialist to consider as a clarification opportunity?

A.

Chronic respiratory failure only

B.

Acute hypercapnic respiratory failure

C.

Metabolic acidosis

D.

Stable COPD without respiratory failure

Full Access
Question # 22

An arterial blood gas shows pH 7.24, PaCO₂ 72 mmHg, and HCO₃⁻ 30 mEq/L in a patient with COPD and acute respiratory distress. Which acid-base abnormality is primarily demonstrated?

A.

Respiratory acidosis

B.

Respiratory alkalosis

C.

Metabolic acidosis

D.

Metabolic alkalosis

Full Access
Question # 23

Two MS-DRGs have relative weights of 0.85 and 2.10. Which statement is MOST accurate?

A.

The 2.10 DRG is associated with greater relative expected resource consumption

B.

The 2.10 DRG guarantees twice the hospital's billed charges

C.

The 0.85 DRG represents a higher risk of mortality

D.

Relative weight measures physician performance rather than resource use

Full Access
Question # 24

The amount of the IPPS Indirect Medical Education Adjustment is determined by teaching intensity as measured by the hospital's number of residents compared to:

A.

ED and inpatient beds

B.

Number of admissions

C.

Inpatient beds

D.

Disproportionate payment rates

Full Access
Question # 25

A patient is admitted with sepsis due to an E. coli urinary tract infection. The provider also documents acute kidney injury due to the sepsis and “severe sepsis without septic shock.” Which sequencing is most appropriate?

A.

Severe sepsis code first, followed by acute kidney injury

B.

Sepsis first, followed by severe sepsis and acute kidney injury

C.

Urinary tract infection first, followed by sepsis

D.

Acute kidney injury first, followed by urinary tract infection

Full Access
Question # 26

A 91-year-old has a past medical history of heart failure, COPD, and adenocarcinoma of the lung and brain. The patient presents with shortness of breath, weakness, and pain. His vital signs are T 99°F, RR 18, BP 108/74, and pulse 110. Pulse oximetry is 98% on 2 L nasal cannula. He is admitted with HCAP, COPD, and diastolic heart failure.

Initial laboratory values are:

Hgb: 9.0

Sodium: 134.0

WBC: 12.9

The physician orders antibiotics and 2 L nasal cannula. Based upon the information provided above, which of the following queries would be MOST appropriate?

A.

Underlying cause and type of pneumonia

B.

Acute blood loss anemia

C.

Acuity and type of heart failure

D.

Corresponding diagnosis for sodium level

Full Access
Question # 27

A hospital had 1,000 inpatient discharges during a reporting period. The sum of the MS-DRG relative weights for those discharges was 1,750. What is the hospital's case mix index (CMI)?

A.

0.57

B.

1.00

C.

1.75

D.

2.75

Full Access
Question # 28

A patient's record contains fever, tachycardia, hypotension, positive blood cultures, and treatment with IV antibiotics and fluids. No corresponding diagnosis has been documented. Which query format is MOST appropriate?

A.

“Does the patient have sepsis? Yes or No.”

B.

“Please document sepsis because the clinical criteria are present.”

C.

A neutral multiple-choice query presenting the clinical indicators and reasonable diagnostic alternatives

D.

No query, because CDI specialists may only clarify diagnoses already documented

Full Access
Question # 29

A CDI specialist reviews a prior hospitalization and finds that the patient previously had chronic systolic heart failure. During the current admission, the provider documents only “history of CHF,” although the patient remains on long-term heart-failure therapy. What is the BEST approach?

A.

Automatically copy chronic systolic heart failure into the current encounter

B.

Use prior documentation as clinically relevant context but obtain current provider clarification when the diagnosis materially affects the present record

C.

Ignore all prior-encounter information under every circumstance

D.

Assign acute systolic heart failure because the diagnosis appeared previously

Full Access
Question # 30

Which of the following programs specifically reduces applicable Medicare payments by 1% for hospitals in the worst-performing quartile based on hospital-acquired-condition measures?

A.

Hospital Value-Based Purchasing Program

B.

Hospital-Acquired Condition Reduction Program

C.

Medicare Shared Savings Program

D.

Inpatient Psychiatric Facility Quality Reporting Program

Full Access
Question # 31

A patient is admitted with a stage 2 sacral pressure ulcer. During the hospitalization, the ulcer progresses and is documented as stage 3 at the same site. How should the pressure ulcer be reported?

A.

Assign only the stage 2 pressure-ulcer code

B.

Assign only the stage 3 pressure-ulcer code

C.

Assign separate codes for the stage on admission and the highest stage reached during the hospitalization

D.

Assign an unspecified-stage pressure-ulcer code because the stage changed

Full Access
Question # 32

Which pressure-ulcer category is specifically included in the traditional CMS HAC payment policy when the condition is not present on admission?

A.

Stage 1 and stage 2 pressure ulcers

B.

Stage 3 and stage 4 pressure ulcers

C.

All pressure injuries regardless of stage

D.

Healed pressure ulcers only

Full Access
Question # 33

Under the IPPS Post-Acute Care Transfer policy, which documentation element is particularly important because it can affect whether transfer-payment methodology applies?

A.

Patient's dietary preference

B.

Discharge disposition

C.

Physician's years in practice

D.

Number of daily progress notes

Full Access
Question # 34

A CDI specialist has been asked to present a report to hospital administration that will demonstrate the CDI program's impact over time. Which of the following reports will BEST accomplish this?

A.

document showing each CDI specialist's query rate

B.

pie graph showing the percentage of queries not answered

C.

PowerPoint presentation outlining the CDI goals and objectives

D.

line graph showing ROM and SOI by month

Full Access
Question # 35

A patient's baseline creatinine is 1.0 mg/dL. Following prolonged hypotension, creatinine rises to 3.8 mg/dL. Urinalysis demonstrates granular casts, and the nephrologist documents “acute renal failure” but does not specify the underlying renal lesion. Which condition would be MOST appropriate to consider in a clinically supported clarification query?

A.

Acute tubular necrosis

B.

Chronic kidney disease stage 5

C.

Nephrotic syndrome

D.

Pyelonephritis

Full Access
Question # 36

A patient's baseline serum creatinine is 0.9 mg/dL. Forty-eight hours after admission, the creatinine is 1.5 mg/dL. Urine output has also decreased. Which condition is most appropriate for the CDI specialist to consider as a clarification opportunity?

A.

Chronic kidney disease

B.

Acute kidney injury

C.

End-stage renal disease

D.

Nephrotic syndrome

Full Access
Question # 37

A physician writes, “respiratory failure following surgery.” The patient required mechanical ventilation for several hours after a prolonged major operation, and anesthesia documentation indicates this was an anticipated part of postoperative recovery. What is the BEST CDI action?

A.

Automatically assign a postoperative respiratory-failure complication code

B.

Query to clarify whether the respiratory failure represents a complication or an expected postoperative condition

C.

Remove respiratory failure from the record

D.

Code acute respiratory failure solely because mechanical ventilation occurred

Full Access
Question # 38

Under the FY 2026 Hospital Value-Based Purchasing Program, hospital performance is organized into which of the following four domains?

A.

Mortality, readmissions, reimbursement, and compliance

B.

Clinical outcomes, person and community engagement, safety, and efficiency and cost reduction

C.

Patient safety, documentation quality, case mix, and physician engagement

D.

Clinical care, claims accuracy, readmissions, and utilization management

Full Access
Question # 39

A patient has a history of a type 2 MI 30 days ago. The patient is admitted for chest pain which is determined to be an NSTEMI. Which of the following diagnosis(es) should be coded to identify the working MS-DRG?

A.

NSTEMI, subsequent MI, chest pain

B.

NSTEMI, initial encounter

C.

NSTEMI, subsequent MI, and Type 2 MI

D.

NSTEMI and subsequent MI

Full Access
Question # 40

A neurologist documents acute cerebral infarction. A qualified stroke nurse records the NIH Stroke Scale score in the medical record. Which statement is MOST accurate?

A.

The NIHSS score cannot be coded unless repeated by the physician

B.

The NIHSS score may be obtained from qualified non-provider documentation when the related diagnosis is documented by the provider

C.

The nurse's NIHSS documentation establishes the cerebral infarction diagnosis independently

D.

NIHSS scores are not reportable in ICD-10-CM

Full Access
Question # 41

The progress note on hospital day 2 of a patient's admission states that the patient got up from the bed to go to the bathroom just after housekeeping had mopped the floor. The patient slipped and fell onto the floor, sustaining a broken wrist. The diagnosis of a fractured wrist will:

A.

Be coded and assigned a POA of “U”

B.

Not be recognized as a CC because it was a hospital-acquired condition

C.

Be considered a CC for calculation of the final MS-DRG

D.

Not be coded because it is a hospital-acquired condition

Full Access
Question # 42

The attending physician documents morbid obesity. A registered dietitian documents a body mass index of 43.6 kg/m² in the nutritional assessment. Which of the following is the MOST accurate statement?

A.

The BMI cannot be coded because it was not documented by the physician

B.

The BMI may be obtained from the dietitian's documentation because the associated diagnosis is documented by the provider

C.

The dietitian's BMI documentation can also establish the diagnosis of morbid obesity

D.

Neither obesity nor BMI can be reported unless both appear in the discharge summary

Full Access
Question # 43

A CDI specialist submits a neutral query regarding possible acute blood loss anemia. The physician answers “clinically unable to determine.” The CDI specialist believes documenting the diagnosis would increase reimbursement substantially. What is the MOST appropriate next action?

A.

Send the same query repeatedly until the physician selects acute blood loss anemia

B.

Change the response to acute blood loss anemia because the clinical indicators support it

C.

Respect the physician's response unless new clinical information creates a legitimate need for further clarification

D.

Ask the coder to assign acute blood loss anemia regardless of the response

Full Access
Question # 44

A patient undergoes colorectal surgery. On postoperative day 2, the physician documents “ileus.” The record shows absent bowel sounds and abdominal distention, but the surgeon also states that delayed bowel function is expected at this stage of recovery. Which action is MOST appropriate?

A.

Automatically code postoperative ileus as a surgical complication

B.

Query the provider regarding whether the ileus represents an expected postoperative condition or a complication

C.

Remove the diagnosis because postoperative ileus is never reportable

D.

Assign intestinal obstruction instead

Full Access
Question # 45

At discharge, the attending physician documents, “Probable aspiration pneumonia causing the patient's respiratory symptoms.” The patient is an inpatient. No subsequent documentation rules out aspiration pneumonia. How should the diagnosis be handled for inpatient coding?

A.

Code only the respiratory symptoms

B.

Code aspiration pneumonia as if established

C.

Query because “probable” diagnoses can never be coded

D.

Code unspecified pneumonia only

Full Access